
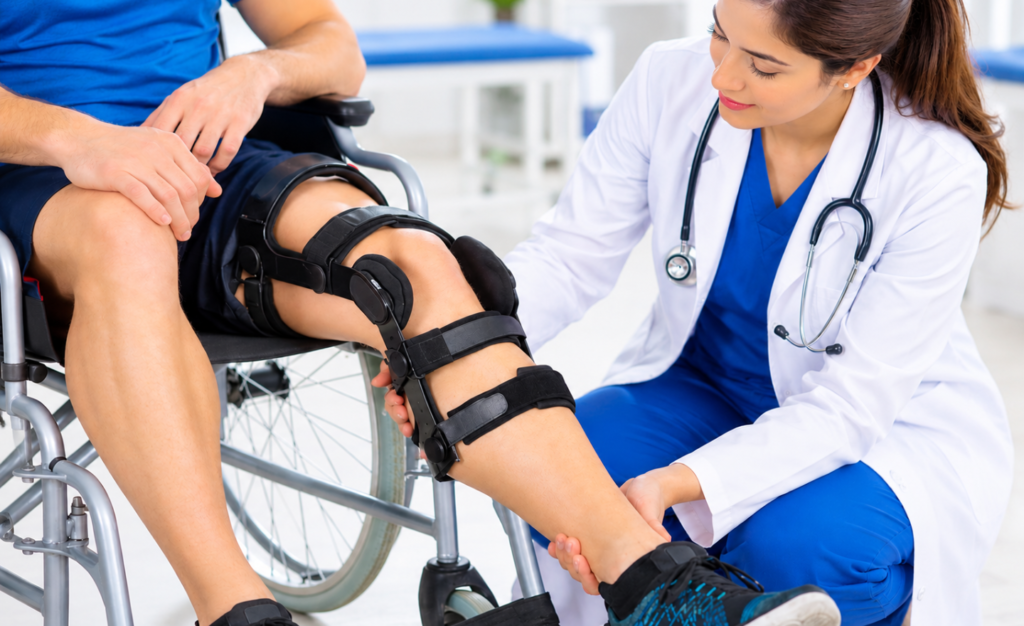
A patient leaves the clinic in a hinged knee brace, and the claim comes back denied as incorrect coding. The brace was right; the L-code, the fitting level or the modifier was not. In-office bracing can be a steady ancillary revenue line for orthopedic practices, but Medicare treats every brace as a DMEPOS item with its own supplier, coding and documentation rules.
This guide covers the three decisions that make or break a brace claim: which L-code to bill, whether the brace is off-the-shelf or custom-fitted, and which modifier the claim needs.
Before the First Brace: Enrollment and Where the Claim Goes
A practice can bill Medicare for braces only if it, or the treating practitioner, is enrolled as a Medicare DMEPOS supplier. Brace claims then go to the DME Medicare Administrative Contractor (DME MAC), not the Part A/B MAC that pays the office visit.
- Separate billing number. Use the practice’s or practitioner’s DMEPOS supplier number, not the Part B group number.
- Separate claim. The visit goes to the Part A/B MAC; the brace goes to the DME MAC.
- Competitive bidding rules. For off-the-shelf back and knee braces, physicians and certain practitioners who furnish the brace as part of a professional service use modifier KV (or J5 for physical and occupational therapists), bill on the same date of service as the visit, and accept assignment (CMS MLN fact sheet, May 2025).
Commercial payers have their own DME contracting. Confirm that your practice is credentialed for DME with each plan before you stock braces for their members.
L-Code Selection: Matching the Brace to the Right Code
The L-code describes the brace’s design and how it was fitted, not the brand. Picking it correctly takes three checks:
- Body region and design. Knee, ankle-foot, wrist-hand, shoulder and spinal orthoses each have their own L-code ranges, split further by features such as hinges, joints and rigid stays.
- PDAC coding verification. For many codes, Medicare pays only for products listed with a coding verification on the PDAC Product Classification List. For knee orthoses this includes L1832, L1833, L1843, L1845, L1851 and L1852. A product not on the list is denied as incorrect coding (DME MAC knee orthoses policy article, 2025 proposed revision).
- Fitting level. Many braces have two codes: one off-the-shelf and one custom-fitted. The next section explains how to choose.
For bilateral braces, bill each side on its own line with RT or LT and one unit. A single line with two units, or without RT/LT, is rejected.
Off-the-Shelf vs Custom-Fitted: Who Fitted It and How
The same brace can be billed as off-the-shelf (OTS) or custom-fitted. There is no physical difference between them; the fitting work decides the code.
| Factor | Off-the-shelf (OTS) | Custom-fitted |
|---|---|---|
| Fitting at delivery | Minimal self-adjustment | Substantial modification for an individual fit |
| Who fits it | No specialized training required | A certified orthotist or someone with equivalent training, such as a physician, PT or OT |
| Documentation | Delivery and patient instruction | What was modified, how, and by whom |
| Example pair | L1851 | L1843 |
If the note does not describe substantial modification, bill the OTS code. Billing custom-fitted codes without that documentation is a frequent audit target; prefabricated knee orthoses are an approved Recovery Audit Contractor (RAC) review topic.
KX, GA, GY and GZ: Which Modifier, When
On a Medicare brace claim, the liability modifier tells the DME MAC whether coverage criteria are met and who pays if they are not. Choose it from the documentation, not from habit.
| Modifier | Use it when | Who pays if denied |
|---|---|---|
| KX | Every coverage criterion in the LCD is met and documented | Not expected to deny |
| GA | Criteria may not be met and a valid ABN is on file | The patient |
| GZ | Criteria may not be met and no valid ABN was obtained | The practice |
| GY | The item is statutorily excluded or outside the Medicare benefit | The patient (no ABN required) |
Add KX to the base code and to each addition code only when the record proves every criterion. For knee braces such as L1832, L1833 and L1851, that means a recent injury or surgery, or knee instability documented by exam with objective findings such as a positive drawer test (Noridian knee orthoses checklist).
Modifier errors are a common cause of brace denials. Our posts on DME modifiers and orthopedic coding modifiers cover the wider modifier set.
Orders, Proof of Delivery and Medical Records
Every brace claim must be supported by records the practice can produce on request. Missing any one of them turns a paid claim into an overpayment.
- Standard written order (SWO): patient name or MBI, order date, item description, quantity, and the treating practitioner’s name, NPI and signature.
- Face-to-face encounter and written order prior to delivery: required for certain knee and spinal codes on CMS’s Required Prior Authorization and WOPD lists. Delivering before the order exists is denied as not reasonable and necessary.
- Prior authorization: some knee and spinal orthosis codes require it for Medicare. Check the current CMS list before dispensing.
- Proof of delivery: signed and dated by the patient at the time the brace is dispensed.
- Medical record support: the treating practitioner’s notes must show why this brace, at this fitting level, is needed.
These records are also what auditors request first. See our guide to orthopedic billing compliance for building audit-ready documentation, and our DME billing FAQ for general DMEPOS questions.
Conclusion: Code the Fitting, Prove the Need
The lesson for any bracing program: code what was actually done. Match the L-code to the PDAC listing for the product, bill custom-fitted only when the note shows real modification, and let the documentation decide the modifier.
If brace claims are being denied or flagged, MBW RCM can help. Our orthopedic billing specialists set up DME billing workflows and review bracing documentation before claims go out.